Individualized Mental Health Care is Essential in Pregnancy

Mental health conditions are real health issues that deserve appropriate and individualized medical care. Making informed healthcare decisions requires that women and their healthcare providers be aware of the available safety information for each specific medication they might be considering. We encourage pregnant women and those planning a pregnancy to have open conversations with their healthcare providers to carefully weigh any potential increased risks of medications, as well as the risks of untreated or undertreated mental health conditions.

SSRIs – including commonly prescribed medications such as Zoloft (sertraline), Lexapro (escitalopram), Prozac (fluoxetine), Paxil (paroxetine), and others – are among the most well-studied medications used in pregnancy. Decades of research have shown that SSRIs, when used appropriately and under the care of a healthcare provider, can be part of an effective treatment plan for managing mental health conditions before, during, and after pregnancy, and can contribute to better outcomes for women and their babies.

As always, MotherToBaby and the Organization of Teratology Information Specialists (OTIS) stand with women and their healthcare teams by providing up-to-date, evidence-based information on the use of medications and other exposures during pregnancy and while breastfeeding.

MotherToBaby offers free, expert-reviewed fact sheets on SSRIs and other medications, as well as on conditions such as depression, anxiety, and stress. You can find many of our mental health resources here: https://mothertobaby.org/pregnancy-breastfeeding-exposures/mental-health/. Individuals can also reach out to a MotherToBaby specialist via phone, live chat, text, or email to receive personalized, confidential support.


Individualized Mental Health Care is Essential in Pregnancy

Understanding Critical Periods in Pregnancy

Kendra, newly pregnant at approximately 7 weeks along, contacted MotherToBaby late one afternoon with a question that had been causing her a lot of anxiety. Norovirus was running rampant in her home, and she was feeling extremely nauseous. Having found relief with it before, she explained that she had taken a single dose of Zofran (ondansetron) early that morning. She was certain this drug was ok to take during pregnancy, but after searching online, she became concerned. Kendra shared that she had read conflicting information about whether Zofran increased the risks for birth defects; with some studies showing an increased chance of heart defect and cleft palate, and other studies showing no increased risk. Feeling confused, Kendra reached out to MotherToBaby with her question to receive personalized information.

On the call, I first explained that birth defects can happen in any pregnancy for different reasons. Out of all babies born each year, about 3 out of 100 (3%) will have a birth defect. Pregnancy problems (like miscarriage) can also happen in any pregnancy. Sometimes, exposures like medications, drugs, alcohol, and infections can increase the chance for birth defects or pregnancy complications. However, for an exposure to cause a problem, it generally has to happen during the “critical period” when a body part is forming.

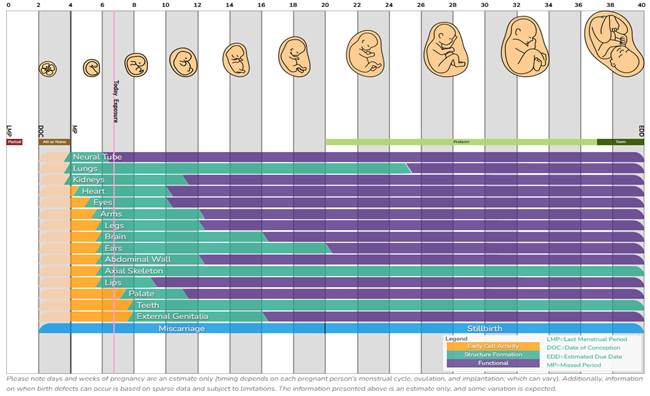
To help Kendra understand more about possible risk from her Zofran exposure, I used MotherToBaby’s new and interactive critical periods of pregnancy tool! This helpful pregnancy calculator and chart shows when different parts of a baby’s body form during pregnancy and when birth defects or pregnancy complications might happen. By entering the first day of your last menstrual period (LMP) or estimated due date (EDD), the calculator can estimate how far along you are today. Individuals who have questions about exposures in pregnancy can then go on to enter the specific date(s) when the exposure (such as medication use or alcohol consumption) occurred, and the chart will show the body parts that are developing during that time.

After entering the first day of Kendra’s last period, the interactive tool confirmed she was 6 weeks and 5 days pregnant. I then entered her Zofran exposure using today’s date, which resulted in a pink line popping up on the chart. Following this line down the chart, I could see all of the different body parts that were currently forming. I explained to Kendra that when she took the Zofran, the palate (roof of the mouth) had not yet started to form, meaning that the medication use was unlikely to increase the chance of cleft palate in the baby. The chart also helped me see that the baby’s heart was currently developing. I shared this with Kendra, but also reminded her that the latest research shows there is thought to be a less than 1% chance of heart defects from exposure to Zofran; meaning there is a more than 99% chance the heart will not be affected by her medication use. In other words, even when an exposure of concern takes place during the critical period, not every baby will be affected by that birth defect. 

New Critical Periods of Pregnancy Interactive Tool

For Kendra, being able to understand which specific body parts were forming when she took the Zofran and whether she actually needed to be concerned helped decrease her anxiety significantly. Knowing that the heart was currently forming, she decided to reach out to her healthcare provider to discuss alternative treatment options for her nausea.  I was happy to have helped answer Kendra’s question using this visual tool and look forward to being able to use it again in the future when pregnant women have questions about the timing of their exposure.

Remember that our team is always available to help review any exposures you have had and provide a personalized risk assessment. Don’t hesitate to contact MotherToBaby by phone, chat, text, or email!


Individualized Mental Health Care is Essential in Pregnancy

Marie called with a question, “My baby is 4 weeks old, and my husband and I love her to death. However, she is a lot of work, and we do not want another little one quite yet. My husband and I are also hoping to resume our sex life, but can I be on birth control while breastfeeding?” 

MotherToBaby is here to help answer some of those questions!  Of course, before you decide, it is best to speak with your medical provider and get their advice.  Since everyone is different, some birth control methods might not be a good match for you.

Can breastfeeding be used as contraception?

There are many benefits to breastfeeding. Breastmilk has antibodies that are passed to the baby and help them build their immune system and protect against illnesses. Breastmilk is also a great source of nutrition. When a woman is breastfeeding, they might experience amenorrhea (when you do not have a monthly a menstrual period). Breastfeeding can be a temporary form of birth control if the person is exclusively breastfeeding (i.e., no formula), they have not had a menstrual period yet, and the baby is less than 6 months old. This method is sometimes called the “lactational amenorrhea method (LAM)”. LAM does not work for everybody and may not be reliable enough for all couples. Some people do not develop amenorrhea when breastfeeding, so another form of birth control would be recommended.

Are there other forms of birth control that I can use when breastfeeding?

Many contraceptive methods do not affect your breastfeeding.  However, options which contain estrogen might reduce your milk supply. Depending on what option you choose, your healthcare team may suggest that you wait up to 4-6 weeks after delivery so that your milk supply is well established, and your body has recovered from childbirth.

Another factor is how serious you are about preventing another pregnancy. Some options such as the IUD, hormonal implant, and Depo-Provera injection are 98-99% effective in preventing pregnancy (this means only 1 or 2 out of 100 women will get pregnant every year using those methods). The birth control pill is around 93% effective in preventing pregnancy (this means around 7 out of 100 women will get pregnant every year using birth control pills). The condom is around 85% effective, depending on how carefully it is used (this means around 15 out of 100 women will get pregnant every year using this method).

The American College of Obstetricians and Gynecologists (ACOG) has a web page that answers frequently asked questions about contraceptives including advantages and disadvantages of each type:  https://www.acog.org/womens-health/faqs/postpartum-birth-control

Hormonal Birth Control Options

There are many kinds of hormonal birth control options including pills taken orally (by mouth), injections, implants, and some IUDs. Some options contain forms of both estrogen and progesterone, and some just contain progesterone. In general, it is expected that only small amounts of the hormones would pass into your breastmilk, and these low levels are unlikely to result in any side effects in your baby. However, some of them can affect your milk supply.

Some estrogen-containing options include “combination birth control pills,” the skin patch, and the vaginal ring. A disadvantage of estrogen is that it can reduce or even stop milk supply. Healthcare providers usually recommend waiting to start estrogen-methods until at least 4 weeks after delivery to allow your milk supply to be well established.

Progesterone-only options include the progestin only pills (“mini pills”), the injection (ex. DepoProvera shot), the implant (ex. Nexplanon), the hormonal intrauterine device (IUD), and emergency contraception. Progesterone only options generally do not reduce your milk supply or affect milk quality. Some professional groups suggest waiting 4-6 weeks after giving birth before getting the Depo-Provera shot because the amount of hormone in your blood and milk from this injection are highest around the time it is given.

Non-Hormonal Birth Control Options

Non-hormonal birth control options include barrier methods like male and female condoms, spermicide, diaphragms, the cervical cap, the sponge, and the copper IUD.  None of these strategies impact milk supply. 

Fertility Awareness Methods/Lifestyle Options

Other birth control options that do not include hormones or barrier items are the calendar tracking option and abstinence. The calendar tracking option is when you track your menstrual cycle and avoid intercourse on the days you are most fertile (most likely to get pregnant). This method is not very reliable following childbirth because a menstrual cycle can be irregular during the first few months. Abstinence is the avoidance of vaginal intercourse and choosing to be intimate in other ways that cannot result in a pregnancy. Abstinence is 100% effective at preventing pregnancy.

Summary

In summary, what is the best birth control option during breastfeeding? Each person will be different, so it is important to talk with your healthcare provider about which option is best for you based on the timing, effectiveness, family planning decisions, and your other personal health factors.

Resources

2023. Postpartum Birth Control; Frequently Asked Questions. American College of Obstetrics and Gynecology. https://www.acog.org/womens-health/faqs/postpartum-birth-control

Berens P, Labbok M; Academy of Breastfeeding Medicine. ABM Clinical Protocol #13: Contraception During Breastfeeding, Revised 2015. Breastfeed Med. 2015 Jan-Feb;10(1):3-12. doi: 10.1089/bfm.2015.9999. PMID: 25551519.

2024. Contraception and Birth Control Methods. Centers for Disease Control and Prevention.  https://www.cdc.gov/contraception/about/index.html

2024. About Breastfeeding. Centers for Disease Control and Prevention. https://www.cdc.gov/breastfeeding/php/about/index.html

Goulding Alison N., Wouk Kathryn, and Stuebe Alison M., Contraception and Breastfeeding at 4 Months Postpartum Among Women Intending to Breastfeed. Breastfeeding Medicine. January 2018, 13(1): 75-80.

Stanton TA, Blumenthal PD. Postpartum hormonal contraception in breastfeeding women. Curr Opin Obstet Gynecol. 2019 Dec;31(6):441-446. doi: 10.1097/GCO.0000000000000571. PMID: 31436540. 


Individualized Mental Health Care is Essential in Pregnancy

Melissa, pregnant for the first time, live chatted with MotherToBaby through our website: “Hi, I’m 29 weeks pregnant and wondering about vaccines. I have seen so many different things online and I am worried about getting really sick while I’m pregnant. Can you help?”

Melissa is not alone. Many people contact MotherToBaby to find the most up-to-date information about vaccines during pregnancy. Protecting yourself from circulating viruses can also help protect your developing baby. Infections such as influenza, pertussis, rubella, chicken pox, and COVID-19 can cause serious problems in both a pregnant woman and her developing baby. Let’s navigate through the current recommendations.

Plan to Receive Some Vaccines Prior to Pregnancy

You may have heard there are some vaccines, like measles, mumps, and rubella (MMR) and chickenpox (varicella), you should not receive during pregnancy. These “live” vaccines are avoided as they are made from viruses or bacteria that have been weakened, but not killed. Due to the small chance that a live vaccine might cause the disease itself, live vaccines are not routinely given to pregnant women.

So how can you protect yourself and your developing baby from viruses like measles, mumps, rubella (MMR) and chicken pox if it is not recommended (also known as contraindicated) to receive the vaccines during pregnancy? The Centers for Disease Control and Prevention (CDC) consider people who have received one or more doses of MMR vaccine during their lifetime to be protected for life. Adults who never got the MMR vaccine should get at least 1 dose (or 2 doses for some people at higher risk of infection) before pregnancy. Those who have never had chickenpox or received a chickenpox vaccine should get 2 doses of varicella vaccine, at least 4 weeks apart, before pregnancy. If you aren’t sure if you ever got vaccinated for MMR or chickenpox or unsure if you had chickenpox in the past, you can safely receive the necessary live vaccines before that positive pregnancy test! Out of an abundance of caution (small possibility of that infection) it is advised to wait at least one month before becoming pregnant after these vaccines. This is just one reason why it is beneficial to have a pre-pregnancy health checkup and to discuss any future conception plans with your provider!

So, which vaccines should you receive during pregnancy?

CDC recommends all women who are pregnant receive the flu shot and updated COVID-19 vaccine each year, a Tdap (tetanus diphtheria pertussis) vaccine in each pregnancy, and an RSV (respiratory syncytial virus) vaccine (if you have not received one in a previous pregnancy).These vaccines are not live vaccines and have not been associated with an increased chance for birth defects or pregnancy complications. (A nasal spray vaccine is also available against influenza, but it is a live vaccine and not recommended in pregnancy).

Influenza vaccine (flu shot)

The flu shot usually becomes available in September and is offered throughout flu season. CDC recommends getting a flu shot by the end of October despite flu seasons varying in their timing each year. This timing helps protect a pregnant woman before flu activity begins to increase. Protection begins about two weeks after you get the flu shot and lasts at least six to eight months. It is necessary to receive the seasonal flu shot each year to be protected in the current flu season. Getting vaccinated during your pregnancy may also help protect your baby from getting sick during the first 6 months of life! This is especially important because infants less than 6 months of age cannot receive the flu vaccine.

COVID-19 vaccine

It is well known that pregnant women are more likely to get very sick from COVID-19 compared to those who are not pregnant. This is why is so important to receive an updated COVID-19 vaccine every year, any time before or during pregnancy, for the best protection against severe illness. CDC recommends staying up-to-date with COVID-19 vaccines every year: https://www.cdc.gov/covid/vaccines/stay-up-to-date.html.

Tdap vaccine

“I just had a Tdap vaccine a couple years ago – so I don’t need another one, right?” Melissa asked a very common question we receive regarding the Tdap vaccine during pregnancy. Although this vaccine is recommended for adults every 10 years, for women who are pregnant, receiving the shot in the 3rd trimester (specifically 27-36 weeks gestation) can help the baby get as many of the mother’s antibodies as possible. After delivery, these antibodies provide some protection against pertussis, also known as whooping cough (a very contagious respiratory infection), until the baby can receive his/her own dTAP vaccine (starting at 2 months of age). Additionally, if everyone who lives with you and any caregivers get the vaccine, it can lower the chance for the baby to be exposed to pertussis.

RSV vaccine

The RSV vaccine protects both pregnant women and their babies from RSV, a virus that can cause serious breathing problems in babies. CDC recommends a single dose of the Abrysvo® RSV vaccine between 32 and 36 weeks of pregnancy, during the RSV season (September-January). As with the flu and Tdap vaccines, this maternal vaccine helps the pregnant woman create antibodies that can pass to the baby, giving the baby some protection from an RSV infection after birth. By getting this vaccine, pregnant women can help keep their newborns safe from serious health complications. Melissa, being 29 weeks, can now plan an upcoming RSV vaccine appointment!

Pregnant women who receive vaccines can also share their experiences with maternal health researchers, like MotherToBaby. Our studies are published in medical journals and product labels, and can help others like you when navigating vaccine decisions in pregnancy.

There are no Vaccines to Prevent Some Infections

Many people are packing their bags for a getaway during the summer months. If you are considering an upcoming vacation or babymoon, it’s important to protect yourself from viruses and infections with the appropriate vaccines for that area. Where are you headed? Check with your healthcare provider regarding any specific travel vaccines you might need. CDC recommends discussing any travel plans with your provider at least 4-6 weeks before your trip. Contact MotherToBaby to check the information on any vaccines your healthcare provider recommends

Viruses like Zika, malaria, and Oropouche can be spread by mosquitos and biting flies (midges). These infections can increase serious risks in pregnancy. Since there are no vaccines to prevent these infections, the safest approach during pregnancy would be to not travel to areas with any possible level of risk. Should you choose to travel, it’s important to protect yourself using the recommended insect repellents among other ways to help prevent bites while traveling.

Although Melissa didn’t have any trips planned for the rest of her pregnancy, she was happy to know about these other infections she wasn’t even thinking about!

Other Precautions

Although masks are no longer required in most public areas, this is still a great way to reduce the risk for infections while around others!  Good hand washing is also the most simple and effective way to prevent the spreading of germs to keep you healthy.

After chatting with Melissa, she decided to make her appointment for her COVID-19 and Tdap vaccines (you can get them at the same time!) and will go in ASAP when the flu vaccine for this season is available. She felt reassured knowing she had decided to give herself and her developing baby the best protection from these illnesses as possible.  “Thank you for all this info! I just want to make the best choice for me and my baby – I feel so much better.”

Do you have questions about vaccines during pregnancy? Call, chat, text, or email MotherToBaby!

References:

https://mothertobaby.org/fact-sheets/vaccines-pregnancy/

https://mothertobaby.org/pregnancy-studies/

https://www.cdc.gov/vaccines/by-age

https://www.cdc.gov/vaccine-safety/about/pregnancy.html


Individualized Mental Health Care is Essential in Pregnancy

Spring break is often associated with young college students flocking to the beaches to take a break from their studies. However, it is now embraced by a diverse crowd, including families with pregnant and breastfeeding women. Spring break typically takes place between March and April each year, leading to masses of people traveling by planes, trains, and automobiles. Fun times are possible for everyone, and we have guidance to increase the chances that your travels and experiences will be comfortable and safe for you and your baby.

Check-In with Your Doctor

For most pregnant women, traveling by airline, train, car, or bus is generally safe until close to their due date. Regardless of your trimester, a quick check-in with your doctor is essential to ensure you are cleared to travel.

  • First Trimester: If you are experiencing pregnancy-related nausea, prepare ahead with needed medications and a plan to stay hydrated.
  • Second Trimester: If you are healthy, this is a great time to travel.
  • Third Trimester: You should be fine to travel, but keep in mind that if you go into early labor, you don’t want to be far from high-quality obstetrical care. Check for hospital locations at your destination.

Check for Infectious Disease Warnings

If you are traveling outside of the U.S., check for disease warnings or recommended vaccines for your destination on the CDC Travelers’ Health page. Additionally, if your destination has mosquitoes, use insect repellants to reduce the risk of exposure to infectious diseases.

Sun Exposure and Heat

Prolonged sun exposure can lead to overheating and dehydration, and in severe cases, heat stroke. High fever is a potential concern for pregnant individuals in any trimester. Prevention is key:

  • Keep hydrated.
  • Protect against direct sun for prolonged periods (sit under an umbrella or go indoors).
  • Use sunscreen.
  • Drink plenty of water.
  • Avoid alcohol and limit caffeine, as they can increase dehydration.

Sunscreen

Everyone, including pregnant and breastfeeding women, should use sunscreen year-round. While there is some evidence that chemical sunscreens can penetrate the body in very small amounts, the American College of Obstetricians and Gynecologists (ACOG) recommends the use of effective sunscreen. For breastfeeding women, remember that sun exposure does not provide enough vitamin D for your baby; the American Academy of Pediatrics recommends 400 IU of vitamin D daily for breastfed babies.

Dietary Concerns

One of the highlights of travel is enjoying local food. For pregnant women, the risks from food-borne illnesses remain the same whether at home or on vacation. Avoid unpasteurized milk products, undercooked meats, and fish from risky categories.

Alcohol

Alcoholic beverages may be a destination goal for many, but pregnant and breastfeeding women are urged to continue following the warnings:

  • Pregnant Women: It is crucial to avoid alcohol, as there is no known safe amount to drink. The risks to the developing baby are significant and can be devastating. Increasingly, restaurants are creating delicious and inviting mocktails (non-alcohol) and other beverages, offering an alternative that does not single out a person from the crowd.
  • Breastfeeding Women: Limiting alcohol is beneficial as it can decrease the amount of breastmilk produced. It is recommended to breastfeed after two hours per drink to reduce the risk of exposure to the baby and developing brain.

Following these recommendations and reminders can help prevent exposures and experiences that could later cause grief and anxiety. Prepare well and enjoy your holiday! Ideally, a well-planned spring break will lift your spirits, provide a mental health break, allow you to enjoy new or favored foods, and create new and wonderful memories.

References and Additional Information:

CDC:

https://wwwnc.cdc.gov/travel/page/sun-exposure

https://www.cdc.gov/niosh/heat-stress/about/illnesses.html

https://wwwnc.cdc.gov/travel/page/sun-exposure

https://www.cdc.gov/breastfeeding-special-circumstances/hcp/diet-micronutrients/vitamin-d.html

https://wwwnc.cdc.gov/travel

ACOG

https://www.acog.org/womens-health/faqs/travel-during-pregnancy